Glucosamine or Collagen for Osteoarthritis? Why an Orthopedist Recommends Something Else
Glucosamine is said to protect cartilage, collagen to strengthen joints. But how much do these supplements actually help with osteoarthritis? Orthopedic surgeon Dr. Florian Pfalzer explains what the research shows, which risks are often overlooked — and what works better than supplements.
When your knees feel stiff in the morning and every step down the stairs hurts, it's tempting to reach for powders and capsules. Glucosamine is one of the most popular options, with products promising to protect cartilage or even help rebuild it. Often combined with chondroitin or compared with collagen, it is widely marketed for joint health. Yet German medical guidelines do not recommend glucosamine for knee osteoarthritis. So why is it still so popular?
Orthopedic surgeon Dr. Florian Pfalzer explains whether glucosamine or collagen offers greater benefits, what the science says about rebuilding damaged cartilage, and why a supplement that seems harmless can pose risks for some people.
Let's say I'm over 50 and my knees are increasingly making themselves known in the mornings. What would you advise?
My first piece of advice is: take your body's signals seriously, but don't panic. Not every knee pain automatically means osteoarthritis. Morning stiffness or start-up pain can be early signs of degenerative changes, but the important thing is to find out early what is actually behind them.
At our sports medicine practice in Stuttgart, we therefore look not only at the joint itself but at the entire musculoskeletal system. What is the muscle strength like? What is the leg axis like? How much load does everyday life place on the joint? What role do body weight and metabolism play?
My most important piece of advice is to keep moving. Joints need movement to stay healthy. Targeted strength training, cycling, or swimming can all be very helpful. And above all: don't wait until symptoms begin to take over your daily life. The earlier we identify risk factors, the better we can address them.
Glucosamine for Osteoarthritis: What Studies Show About Its Effects
Glucosamine is marketed in drugstores and online as a "joint savior." What is the truth behind that claim?
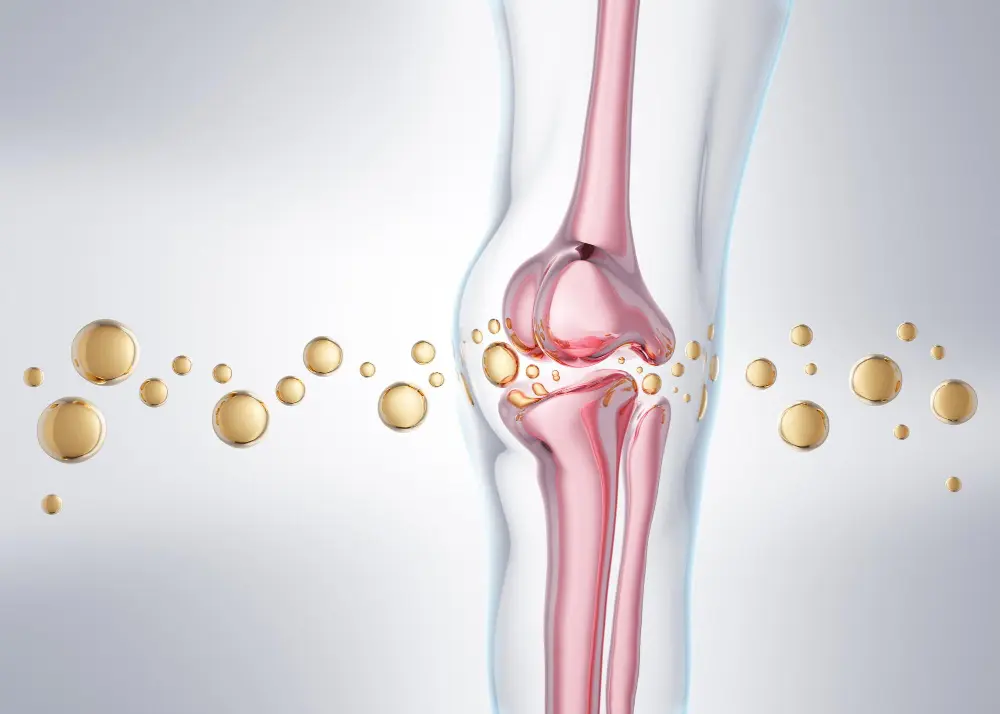
Glucosamine is a naturally occurring component of certain structures within cartilage tissue. This gave rise to the idea that taking additional glucosamine could protect or even regenerate joint cartilage — which sounds plausible at first. However, biological plausibility does not automatically translate into clinical efficacy.
The scientific evidence presents an inconsistent picture. Some studies — particularly those involving certain pharmaceutical glucosamine sulfate preparations — report a degree of pain relief. Other high-quality studies, however, find no meaningful advantage over placebo.
I therefore advise my patients against thinking of glucosamine as a kind of joint insurance.
Some manufacturers even claim that glucosamine rebuilds cartilage. Is that actually possible?
As an orthopedic surgeon, I am very clear on this point: there is currently no convincing scientific evidence that taking glucosamine can rebuild already damaged joint cartilage. Cartilage is a highly specialized tissue. It has no blood supply of its own and therefore has only a very limited capacity for self-repair.
We also need to distinguish between an improvement in symptoms and actual cartilage regeneration. The fact that a patient experiences less pain does not mean that new cartilage has formed.
Modern regenerative orthopedics is actively exploring ways to positively influence the biological environment of the joint. These include approaches such as platelet-rich plasma and cell-based therapies.
But even here, the same principle applies: promising biological mechanisms are not yet proof of clinically relevant cartilage regeneration. My goal is to draw on medical innovations without giving patients false hope.
Collagen for Osteoarthritis: What Research Shows So Far
Is collagen or glucosamine better for joints?
That is actually a question I get quite often. The two substances work in different ways. Glucosamine is involved in building cartilage components, while collagen is an essential structural protein of connective tissue, and therefore also of joint cartilage.
For certain collagen preparations, there are smaller studies suggesting a possible improvement in joint complaints. However, the studies vary considerably in terms of preparations, dosages, and methodological quality.
The data on glucosamine are equally contradictory. At present, we do not have scientifically convincing evidence that collagen is fundamentally more effective than glucosamine for osteoarthritis.
I would therefore not recommend either supplement as a blanket solution. What matters far more to me is that patients get enough protein, train their muscles, and improve their metabolic health. When it comes to joint health, strong muscles are often worth more than an expensive supplement.
Medical guidelines advise against glucosamine, yet it is still available in pharmacies as a licensed medication. How does that add up?
This is an important point that frequently causes confusion among patients. A clear distinction must be drawn between regulatory drug approval and current medical treatment recommendations.
A licensed medication meets certain regulatory requirements. However, that does not automatically mean it belongs among the preferred treatment options according to the current state of scientific knowledge. Guidelines evaluate the totality of available studies and take into account, among other things, the actual benefit for patients.
The current German S3 guideline for gonarthrosis does not recommend glucosamine because a clear clinical benefit has not been sufficiently demonstrated. On top of that, different glucosamine preparations vary in their composition and pharmaceutical quality.
I therefore always make this clear to my patients: the fact that a preparation is available at the pharmacy does not mean it is the best therapy for your condition. What matters to me is individualized treatment guided by scientific evidence — not advertising promises.
Glucosamine is often sold in combination with chondroitin. Does the combination offer any additional benefit, or is it simply a marketing strategy?
Glucosamine and chondroitin are both components and building blocks of the cartilage matrix, so combining the two initially seems logical. The key question, however, is not whether the combination sounds theoretically sensible, but whether patients actually benefit from it.
And here, the scientific evidence remains contradictory. Some studies show positive effects on pain or certain structural measurements, while other high-quality studies are unable to confirm these findings.
Convincing evidence that the combination is clinically superior to a single active ingredient — or that it regenerates damaged cartilage — is lacking. I therefore view such combination preparations with skepticism, particularly when they are marketed with sweeping promises of cartilage regeneration. Two active ingredients do not automatically mean double the effect.
Why Glucosamine Is Not as Harmless as Many People Think
"Natural" does not automatically mean harmless: for whom can glucosamine become a problem?
The word natural gives many people an automatic sense of safety. But even natural substances can produce side effects or interact with medications.
Patients who take certain anticoagulant medications should be especially cautious. Interactions associated with an increased risk of bleeding have been reported, particularly with vitamin K antagonists such as warfarin. People with diabetes should also speak with their doctor before taking it. There are indications of possible changes in blood sugar levels, although the evidence on this point is not conclusive.
For people with a shellfish allergy, the origin of the specific preparation also needs to be taken into account. During pregnancy and breastfeeding, sufficient safety data are lacking. Gastrointestinal complaints may also occur.
That is why in my practice I ask not only about prescription medications but explicitly also about dietary supplements. Something that is available over the counter is not automatically suitable for everyone.
What mistake do you see osteoarthritis patients making again and again in your practice?
The most common mistake is that patients, out of fear of pain, progressively cut back on physical activity. This often leads to a genuine vicious cycle: less movement means less muscle strength, poorer joint stability, and in the long run, frequently even worse symptoms.
A second mistake is viewing osteoarthritis purely as mechanical wear and tear. We now know that osteoarthritis is a disease of the entire joint. Beyond the cartilage, the underlying bone, the synovial membrane, inflammatory processes, and metabolic factors all play an important role.
That is why treating only the pain is not enough. We need to improve the entire biological and functional environment of the joint — and that is precisely where I see a key opportunity in modern orthopedics.
What Works Better Than Pills and Powders for Osteoarthritis
The big question for many people affected: can osteoarthritis be slowed down or even stopped?
A precise medical distinction has to be made here. Already destroyed joint cartilage cannot be reliably restored with today's established conservative therapies. Nor can we promise to stop osteoarthritis entirely.
What we can do, however, is positively influence the course of the disease, reduce symptoms, and often preserve joint function for many years. Particularly important are muscle building, a healthy body weight, regular exercise, and addressing any underlying metabolic and inflammatory factors.
We are also working intensively with regenerative and orthobiological procedures such as PRP therapy and stem cell therapy, in which the body's own blood components or components derived from fat cells are used. For PRP and stem cells, there is evidence — particularly in knee osteoarthritis — of improvements in pain and function. Confirmed cartilage regeneration, however, has not been demonstrated.
What actually helps your osteoarthritis patients when pills and powders alone are not the answer?
I am convinced that osteoarthritis today needs to be treated far more comprehensively than it was a few years ago. At our sports medicine practice in Stuttgart, we therefore take an individualized approach that brings together modern diagnostics, functional therapy, prevention, and — for suitable patients — regenerative treatment methods.
It starts with a thorough analysis. We look not only at X-rays or MRI findings, but also at muscle strength, movement patterns, body composition, and individual risk factors.
Where needed, we complement these measures with individually tailored pain management. For selected patients, joint-preserving procedures such as hyaluronic acid injections may also be considered. We are always transparent about the fact that the scientific evidence varies and that not every approach is right for every patient.
What matters most to me, however, is the long-term perspective. I like to speak of joint longevity — the sustained health of our joints over time. We invest enormously today in cardiovascular health, metabolism, and healthy aging. Our joints deserve the same priority. After all, what is the point of a long life if we can no longer move freely and independently without pain?
My goal is therefore not only to relieve patients of pain in the short term, but to preserve their mobility, resilience, and quality of life for as long as possible.
Regenerate rather than replace — and above all, act early, before joint replacement ever becomes a question.